
Your doctor has recommended that you have an Endoscopic Submucosal Dissection (ESD) in the oesophagus (gullet) or stomach. This leaflet will explain the procedure and what to expect on the day of your procedure. If you have further questions, please telephone the department or discuss them with a member of staff on the day of your procedure.
What is an Endoscopic Submucosal Dissection (ESD) of the upper digestive tract?
ESD is a procedure where a lesion or polyp is removed from either your oesophagus (gullet) or stomach.
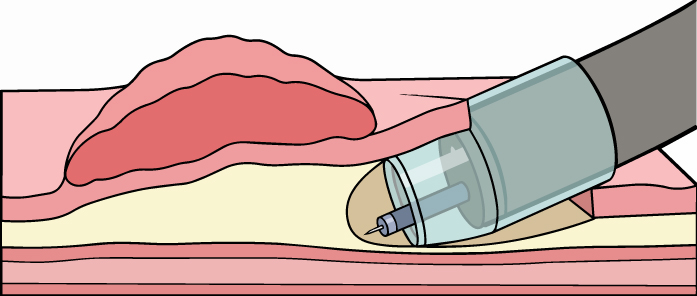
The procedure will be carried out using a gastroscope (flexible camera) that is passed through the mouth to access the area of irregularity. The procedure is usually performed under general anaesthesia. When the lesion or polyp has been located, it is raised by injecting fluid into the tissue underneath. The injection increases the thickness of the gut wall, making it easier and safer to remove the lesion. The lesion is then removed using diathermy (heat treatment), which allows the lesion along with some of the tissue underneath to be cut and removed. You will not feel this.
Why am I having an ESD of the upper digestive tract?
Your previous endoscopy or test has found a lesion or polyp in your oesophagus (gullet) or stomach. In most cases, the biopsies (small samples of tissue) have indicated the lesion or polyp requires removal as a single fragment. Removing the lesion in one piece gives the pathologists (the doctors who examine the lesion under the microscope) the greatest opportunity to know if it has been fully removed.
All tissue samples have to be sent away to the laboratory so the results will not be available straightaway. You will be able to discuss the results of your ESD with the doctor who referred you.
What are the benefits of having an ESD of the upper digestive tract?
The main benefit of this procedure is that the lesion can be completely removed without the need for a major operation. In the majority of cases, the ESD is performed as a day case procedure, which means that you are discharged after a few hours of observation, following the procedure. Time taken to recover and discomfort after the procedure is far less when compared with surgery.
What are the alternatives to having an ESD of the upper digestive tract?
Alternative treatments may already have been discussed with you. One alternative is to remove the lesion or polyp using a similar technique known as Endoscopic Mucosal Resection (EMR); however, during EMR, there is less chance of removing the lesion or polyp in one piece and also not removing enough of the normal tissue underneath the lesion or polyp. This makes analysis under the microscope very difficult and introduces uncertainty as to whether the lesion or polyp has been completely removed.
Other options include “keyhole” or “open” surgery, which means an operation. This is generally associated with a longer recovery and may carry greater risks. Alternatively, you may opt not to have the lesion or polyp removed and instead keep it under close review; however, this decision must be carefully considered after discussion with your consultant.
What are the risks of having an ESD procedure?
The most common side-effect following an ESD is a sore throat for a day or two. Less commonly, you can experience rare reactions to the drugs used for sedation or anaesthesia. Very occasionally, there can be damage to crowned teeth or bridgework.
There are known adverse effects from the intravenous drugs administered during the procedure, ranging from mild and common to rare and serious. These include: headaches, nausea, fainting, depression of respiratory and nervous system, which may result in aspiration pneumonia, anaphylaxis and coma. Although these serious complications are rare, they are more common in patients with deeper sedation and / or general anaesthesia.
Two more serious risks are bleeding during, or after the ESD, and perforation (making a hole) in the oesophagus (gullet) or stomach wall. This usually occurs during the procedure and is dependent on the size and location of the lesion or polyp being removed.
Bleeding: This is usually minimal unless you take medication to stop blood clots from forming. Examples of such medications include: Aspirin, Clopidogrel (Plavix), Dabigatran, Edoxaban, Ticagrelor, Dipyridamole (Persantin), Warfarin, Heparin, Rivaroxaban (Xarelto) or Apixaban (Eliquis).
In most cases, bleeding following an ESD will settle on its own without the need for intervention. If the bleeding does not stop, it can be managed by delivering therapy through the gastroscope (flexible camera) without resorting to an emergency operation. If there was bleeding, you would be advised to stay in hospital for an extra few days to make sure the bleeding does not restart. Late bleeding can happen for up to 2 weeks after the procedure, see the end of this leaflet for how to recognise late bleeding following your ESD and what to do.
Perforation: Perforation (making a hole) during an ESD can happen but the risk is small. If your oesophagus or stomach wall is perforated, this can be managed in two ways:
- It may be possible to close the perforation completely using endoscopic clips, in which case, the recovery is usually very quick and you may be able to go home on the same day. If a longer period of observation is required, you will be managed in hospital with intravenous fluids and antibiotics.
- Very rarely, an emergency operation may be required to surgically repair the site of perforation if endoscopic closure is not possible.
A recognised late complication is stricturing (narrowing) of the oesophagus (gullet) after ESD. This usually begins to develop 2 or more weeks after the procedure. The first sign is that swallowing becomes difficult and food or water may feel to get stuck in the food pipe.
In some instances, this may cause vomiting. Please contact your consultant or the Endoscopy Unit if you develop these symptoms. If you have developed a stricture, this can usually be widened endoscopically (via our flexible camera) as an outpatient, without being readmitted to hospital.
What preparation will I need?
All ESD procedures must be performed on an empty stomach. Your appointment letter will tell you when you need to stop eating and drinking. This is very important. We may have to cancel the procedure if we find food or fluid in the stomach as we will not be able to see the lesion or polyp clearly.
Do I keep taking my tablets?
You must keep taking any essential tablets unless your doctor tells you specifically not to.
If you are diabetic, this should have already be highlighted by your referring doctor and you should receive additional information in the post of what to do with your medication, and the steps you need to take to prevent hypoglycaemia (low blood sugar).
- Please telephone the Endoscopy Unit if you have sleep apnoea or are taking tablets that prevent blood clots. Examples include: Aspirin, Clopidogrel (Plavix), Ticagrelor, Dipyridamole (Persantin), Dabigatran, Edoxaban, Warfarin, Heparin, Rivaroxaban (Xarelto), or Apixaban (Eliquis).
What should I bring on the day?
Please bring a list of medications that you take and also any medications that you may require, whilst in the department such as GTN spray, inhalers and / or insulin.
Please do not bring valuables to the department or wear lots of jewellery. Please also ensure that you remove nail varnish as this interferes with the signal received from equipment we use to measure your oxygen levels. If you are staying in hospital, please bring an overnight bag and any medications that you take with you.
You may wish to bring your dressing gown and slippers. You will be asked to change into a hospital gown that is open at the back, before your procedure.
Will I be asleep for my ESD?
ESD’s of the oesophagus (gullet) or stomach will be carried out under general anaesthetic (GA). This is because the procedure normally takes 1 – 2 hours and requires the patient to be as still as possible. Before your procedure, you should be seen in clinic by the team performing your ESD and also attended a pre-assessment clinic, where you will be assessed for fitness for a general anaesthetic.
What will happen on the day of the test?
When you arrive at reception in the Endoscopy Unit, your personal details will be checked. The assessment nurse will collect you and take your medical history, discuss and explain the procedure, and take your blood pressure and pulse. You will be asked for your consent form (supplied with this leaflet).
This will be attached to your notes and taken to the procedure room. Please make sure that you have read this through before you come for your procedure as when you sign your consent form, you are agreeing that this is the procedure you want. Remember, you can change your mind about having this procedure at any time. The endoscopist will discuss the consent form with you.
There may be a wait before you have your ESD as we may need to confirm that a bed is available for you after the procedure. The nursing staff will keep you informed about when a bed may be available for you, if this is required.
Please bring all your belongings with you into the procedure room.
The doctor who will be performing your ESD will meet you before the procedure. You will be able to ask any questions and discuss any worries you may have. The anaesthetist will also see you in the Endoscopy department before the procedure and will discuss the general anaesthetic with you.
Please note:
Every effort will be made to see you at your appointment time; however, due to hospital inpatient emergencies, delays may occur. The Endoscopy staff will keep you informed of any delays.
What happens in the procedure room?
You will be greeted by two nurses who will remain with you during the procedure. The team in the room will complete a checklist to ensure all your information is correct. You will also be asked to remove any dentures or glasses and to lie down on a trolley. A cannula will be placed in your vein so that anaesthetic medication can be administered and an oxygen mask will be placed on your face before you go to sleep. Once you are asleep, you will be positioned onto your left-hand side and a mouth guard placed between your teeth before we start the procedure.
Please note:
All hospitals in the trust are teaching hospitals and it may be that an endoscopist training to do ESD performs your procedure under the direct supervision of a consultant. Student nurses, doctors or medical representatives involved with the equipment used during the procedure may also be present during your procedure to observe the test. If you do not wish them to be present, please inform the endoscopist.
What happens after the test?
You will be woken up in the room, once the endoscopist has finished and then be transferred into the recovery area. The length of your stay in recovery will be dependent on how you recover from the procedure. The nurse in the recovery room will monitor you during your recovery, prepare you for discharge and give you after-care instructions. This can take 2 – 3 hours.
You will be allowed home when the nurse and anaesthetist are happy that you are ready to be discharged.
If you are staying in hospital after your ESD, you will be transferred to the ward when you have recovered.
Most patients feel some discomfort in the chest or upper abdomen for a few days following the procedure and the Endoscopy Unit will provide you with an information sheet of the best way to manage this. You will be able to restart most of your normal medications immediately following the procedure. If you are taking blood thinning medications, the endoscopist will decide when it should be safe to restart this medication.
Will I need to stay in hospital after my ESD?
The procedure is usually undertaken as a day case, but sometimes, the doctor will make the decision that you need to stay in hospital after your ESD for further observation.
You will normally be informed about this in advance when you undergo pre-assessment.
In rare cases, the complexity of the procedure may indicate that you need to stay in hospital for a night for further observation, to ensure you have no problems after your procedure but we will not know this until after the procedure is complete.
Your appointment letter will inform you if you are required to stay in hospital. If you do, you should arrange for someone to be available to collect you from the ward the following day.
If you are not staying in hospital, you will need an escort with you and must only go home in a car / taxi (not public transport) as you may be unsteady on your feet.
Remember: following a general anaesthetic, you will need an escort with you, transport home and someone to look after you for 24 hours after the procedure.
The following restrictions apply to sedated patients only:
Do not
- drive a vehicle;
- drink alcohol;
- operate machinery;
- go to work; and
- sign legal documents.
If you are unable to make these arrangements, please contact the Endoscopy Unit for advice as we may need to arrange a hospital bed for the night.
When will I get my results?
You will receive a copy of the endoscopy report before discharge and this will also be sent to your consultant and GP.
The removed lesion will be looked at under the microscope and the result of this will normally be available 2 – 4 weeks following the procedure. You will be contacted with these results, either by a letter, or you may be asked to attend a clinic.
All enquiries regarding your outpatient appointment should be directed to your consultant’s secretary. If you feel that you are waiting a long time for an appointment to discuss your results, your GP will also have a report so you can see them too.
What should I do if I become unwell after the procedure?
Bleeding or perforation can occasionally present up to 2 weeks after the procedure has taken place. If you experience any severe pain in the abdomen not relieved by passing wind, nausea, vomiting, or bleeding fresh or altered blood via your back passage following your procedure, you should go to your nearest Emergency department and bring the copy of your endoscopy report with you so the doctors know what procedure you have had.
This leaflet has been designed as a general guide to your procedure. If after reading this, you have any questions that you feel have not been answered, please contact the Endoscopy department on the numbers below.
Administration Team
For any enquiry about your appointment including cancellation. Also, contact this number if you require an interpreter or transport.
Monday – Friday, 9.00am – 4.00pm

Nursing Team
Please contact this number if you would like advice on your medication or any other medical question or worry.
Monday – Friday, 9.00am – 4.00pm